|
Other Nelson Articles: Wolves in Sheep's Clothing? More Nelson Articles:     |
PART 5
By Kelleigh
Nelson
April 10, 2013 NewsWithViews.com
"... we
must be wary of those who are too willing to end the lives of the elderly and
the ill. If we ever decide that a poor quality of life justifies ending that
life, we have taken a step down a slippery slope that places all of us in
danger. There is a difference between allowing nature to take its course and
actively assisting death. The call for euthanasia surfaces in our society
periodically, as it is doing now under the guise of "death with dignity" or
assisted suicide. Euthanasia is a concept, it seems to me, that is in direct
conflict with a religious and ethical tradition in which the human race is
presented with " a blessing and a curse, life and death," and we are instructed
'...therefore, to choose life." I believe 'euthanasia' lies outside the commonly
held life-centered values of the West and cannot be allowed without incurring
great social and personal tragedy. This is not merely an intellectual conundrum.
This issue involves actual human beings at risk..." —C. Everett Koop, M.D.
* *taken from the book KOOP, The Memoirs of America's Family Doctor by C.
Everett Koop, M.D., Random House, 1991
Florence Wald and American
Hospice
Florence Wald
is the most famous leader of the modern American hospice movement. She was born
Florence Sophie Schorske in New York on April 19, 1917. She
received a B.A. from Mount
Holyoke College in 1938 and an M.N. from Yale
School of Nursing in 1941. She received a second master's degree from Yale
University in mental health nursing in 1956, and became an instructor at the
school's nursing program. In 1959, she became Dean of Yale's School of Nursing.
The Yale School of Nursing was founded in 1923 with funding from the Rockefeller Foundation.
Wald's
entrance into hospice came about after she attended a 1963 lecture at Yale by
Dr. Cicely Saunders, founder of St. Christopher's Hospice in London. Saunders'
lecture emphasized minimizing pain in terminal cancer patients so that they
could focus on their relationships and prepare for death. Wald immediately began
reshaping the nursing school curriculum to put more focus on patients and their
families and to emphasize care of the dying. Feeling further effort was
required, Wald resigned as dean and went to London to study at St.
Christopher's. Upon her return, she organized the first U.S. hospice in Branford
in 1971. Connecticut Hospice, which began by offering in-home care but
eventually built its own inpatient facility, became a model for hospice care
here and abroad.
Florence Wald,
an agnostic and secular humanist, was an open advocate of euthanasia and
assisted suicide, while Saunders, a devout Christian, opposed the practice and
believed hospice made it unnecessary.
As productive
and influential as Florence Wald was, she sharply disagreed with Dame Cicely
Saunders' life-affirming approach to end-of-life care and said: "I know
that I differ from Cicely Saunders, who is very much against assisted suicide. I
disagree with her view on the basis that there are cases in which either the
pain or the debilitation the patient is experiencing is more than can be borne,
whether it be economically, physically, emotionally, or socially. For
this reason, I feel a range of options should be available to the patient, and
this should include assisted suicide."
So, is Wald
saying assisted suicide should be made available for society's economic needs?
Or perhaps she's referring to the family's inheritance? Economic because it
costs the family too much or the health care system too much? Social reasons
because a dying family member is a stressful situation on the family?
Wald's
pro-euthanasia type of hospice is what is being delivered in many parts of this
country, though many hospice professionals will strongly deny that. Those who do
remain faithful to Dr. Saunders life-affirming vision, who relieve the suffering
of the dying until a natural death occurs in its own timing, will say they do
not hasten death. Those who do hasten death will say the same. The public often
has no way of knowing which type of hospice their loved one will
experience.
Many hospice
leaders have spoken out against euthanasia and assisted suicide, and the whole
American hospice movement has rapidly expanded since its inception. In 1983,
Congress required Medicare to pay for hospice care, which put the treatment in
mainstream medical practice. According to the Center for Nursing Advocacy, in
2010 over 5,100 hospice programs served nearly 1.6 million patients a year in
the United States.
Hospice was
once a grass-roots, home-based model of end-of-life care, but is now part and
parcel of corporate medicine. In 2005, for-profit organizations accounted for
half of all hospices, and they charted profits of about 12 percent from 2001 to
2005, according to the Medicare Payment Advisory Commission. (MedPAC) [Link]
Hospices that
remain true to the Cicely Saunders' life-affirming mission will not hesitate to
proclaim the sanctity of life, while they intervene to relieve suffering at the
end-of-life. Those for-profit and volunteer hospices that are willing to hasten
death normally do not speak about the sanctity of life, and they do not teach
their staff to never impose death. In fact, their training results in quite the
opposite. The hospice industry has marketed itself as this "compassionate thing"
that exists all over the country and is filled with angelic staff who care and
work the kind of wonders Dame Saunders encouraged.
There are
thousands of stories of wonderful care received from hospices and how the
patient and the family have benefited. There are also thousands of stories of
patients being put to an early death by overdosing with pain cocktails or by
dehydration and starvation. There has been a very slick, sophisticated and
well-financed campaign to completely twist the positive contributions of hospice
into something the public would never openly accept.
To be
perfectly clear, water and sustenance are not heroic efforts to keep the dying
alive. This is keeping the patient comfortable. When sustenance cannot be
delivered, at least hydration can be given to keep the body comfortable.
However, there comes a point where the patient's body shuts down, and neither
food nor water are desired or taken and death is imminent. [Link]
Palliative Care and
Terminal Sedation
Palliative
care is not exclusively practiced in a hospice. It is the specialization in the
field of medicine which relieves the distressing symptoms of any serious illness
at any stage of life, whether terminally ill or not. The
World Health Organization states that:
Terminal or
palliative care is used by a majority of hospices today. This often involves
permanently sedating the patient, allowing the patient to dehydrate and die. It
looks outwardly peaceful as the patient is made to sleep in a medically-induced
coma, but the patient's death is the result.
Terminally-sedating the patient is something that can be done in hospice that doesn't outwardly appear like euthanasia where a lethal agent is given. (Morphine is the potent opiate which directly effects the central nervous system. It has neurotoxic effects on the brain. Overdoses lead to asphyxia and respiratory depression. It slows metabolism, causes incontinence, and has acute and chronic effects on the endocrine system, blood, the heart and lungs. The hospice "cocktail" usually consists of Ativan, Haldol and Morphine). It also doesn't outwardly appear like assisted suicide where a patient takes a lethal medication prescribed by a physician. Terminal sedation is more subtle and deceptive. This is what happened to my friend's relative who I told about in Part 3. The man wanted to be with his family, but food and water was denied by hospice. (Yes, there are hospices that refuse to give any food or water and you must sign on to that when they are hired.) The sedating "cocktails" were given to the point where respiratory function was decreased enough to cause early death. 
Palliative
medicine is commonly used by hospice to relieve many symptoms of the dying
patient. It is precise and tuned especially for each patient's illness. However,
there are facilities wherein every patient is sedated because all the patients
are "agitated." It is a perversion of hospice as well as palliative care. It is
a deliberate railroading of patients to an imposed death, a hastened death
through "palliative" or "terminal" sedation.
Surprising to
many, terminal, palliative or "total" sedation is so commonly used today to
hasten death (a method of stealth euthanasia) that it is defined by the
pro-euthanasia Compassion and Choice's "Good to Go Resource Guide" glossary. They define it
as:
Unfortunately,
it is used way too often on patients who are not having severe, intractable
symptoms that cannot be controlled while they are conscious.
Ron Panzer of
Hospice Patients
Alliance states, "In many cases, the Adult Protective Service system is
even used to intimidate those who truly care about the patient and object to
clinically unnecessary or harmful interventions. These can be as common as
giving morphine when there is no pain, sedating a patient who is not agitated,
depriving the patient of needed medications when they are still benefiting from
them or not providing food and fluids as needed when they patient is still
benefiting from them. We have received many calls from families who tell us the
hospice falsely accused them of being a threat to their own loved one and called
APS when they voiced their objections to the death-protocols being implemented
at the hospice. So we have those who truly care about the patient being accused
of being a threat, and those who hasten death in charge of the agency entrusted
to care for the patient!"
Euthanasia Society and
Hospice
Many
supporters of the sanctity of life simply do not know how deep this all goes and
how successful the heirs of the original Euthanasia Society of America have been
in our nation. They do not know how the Euthanasia Society is connected
with the largest segment of the hospice industry in America, and when
some have finally understood it, they have been shocked. Most of those who
affirm the sanctity of life view hospice as the rightful alternative to
euthanasia and assisted suicide. Sadly, this is becoming a rarity.
The largest
hospice organization in our nation is the successor organization to the
Euthanasia Society of America. According to the most prominent hospice leaders
in the world, many hospices in the United States today have no reservations
about hastening death through "terminal sedation," or "palliative sedation." Federal
regulations governing hospice are far fewer in number than those protecting
patients in nursing homes or hospitals, or that state agencies inspect hospices
less frequently than nursing homes or hospitals. Some hospices may go years
without being inspected at all. Because of the HIPAA privacy regulations, nobody interested in researching
what is actually going on in hospice can get access to the data, so hospices
that have an agenda can act without any outside interference or
supervision.
Unlike Dame
Cicely Saunders, a majority of leaders at the top of today's hospice certainly
look nothing like the sanctity-of-life hospice Dr. Saunders founded, yet they
pretend to be. They are what we call utilitarians, interested in the profits,
and expansion of their influence and business. The leaders at the top of the National Hospice & Palliative
Care Organization ("NHPCO") are the Euthanasia Society of America's heirs
and benefactors philosophically. The NHPCO is legally and corporately the final
successor organization of the Euthanasia Society in the very strictest sense of
the terms.
The Euthanasia
Society of America successors, especially in hospice, are now proceeding with
their plan to implement stealth euthanasia for citizens whose "quality of life"
is deemed "unworthy of life." The elderly and severely disabled are the targets,
which feeds right into Obama Care. They don't and won't have to be the "very"
elderly or "very" disabled. With Obama Care it will be the "not-so-elderly"
(even 60 years old) or disabled, being placed in hospice and dying shortly
thereafter, even though they had no terminal illness at all. Others have warned about these developments:
"In an era
of cost control and managed care, patients with lingering illnesses may be
branded an economic liability, and decisions to encourage death can be driven by
cost. As Acting U.S. Solicitor General Walter Dellinger warned in urging the
Supreme Court to uphold laws against assisted suicide: "The least costly
treatment for any illness is lethal medication."
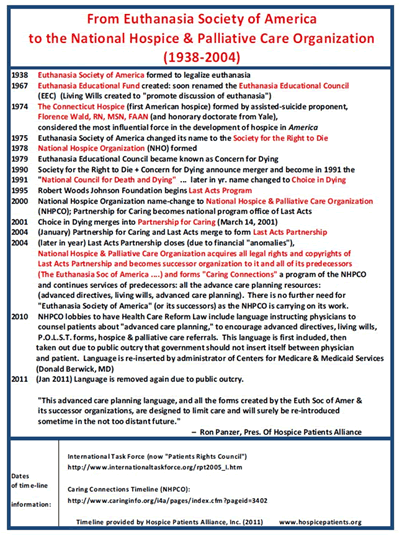
Here is the
succession of name changes the Euthanasia Society of America has gone through.
It is from Ron Panzer's book, "Stealth Euthanasia, Health Care Tyranny in
America."
Several people
who work with the elderly and dying have contacted me with first hand stories of
what they've seen with hospice care. Others have been family members who have
witnessed the lack-of-care in nursing homes and hospitals, as well as the
euthanasia tactics of many hospice care givers. Still, some have been treated to
wonderful care, the sanctity-of-life treatment Dame Cicely Saunders wanted for
all of us who will eventually face death.
In Part 6,
we'll look at the origin of "Living Wills," the changes to Medicare/Medicaid,
and the non-profit and for-profit Hospice organizations and salaries.
~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~~
| |||||||||||||
Thursday, April 11, 2013
Using Sedation To Kill People




Saturday, March 30, 2013
Open Wide And Say Moo!
I wrote about this book a while back and I just found out that it is available on Kindle. I don't have a device that can do this for me, so I'm hoping some of my friends who read this can buy it and let me know how good it is. If this comes out in hard bound I will get it. Dr. Rich is really good as a writer!
Amazon.com: Open Wide and Say Moo! The Good Citizen's Guide to Right Thoughts and Right Actions under Obamacare eBook: Richard N Fogoros: Kindle Store
Amazon.com: Open Wide and Say Moo! The Good Citizen's Guide to Right Thoughts and Right Actions under Obamacare eBook: Richard N Fogoros: Kindle Store
Sunday, March 24, 2013
Great Link on Medical HARM
A friend of mine sent me this link: When Harm in the Hospital Follows You Home - ProPublica It's fabulous. Be sure to read the comments.
Thursday, March 21, 2013
I'm Sorry For The Anesthesia Nurses!
Well, maybe I'm not so sorry for them after all. My original crna, the one who pretended to be a doctor, the one who gave me Versed and general anesthesia against my will in the face of my continued refusals and without a signed "informed" consent, that one? Well, he is the person responsible for me being here. Why would I feel sorry for him? Maybe because he thinks he can read minds (psychic abilities) and "knows what's best" for people he has never met before in his life, even when it turns out badly? Aren't we supposed to feel sorry for people who suffer from delusions? I'm not feelin' it...
Anyway, I found this post on www.hospitalsoup.com in the colonoscopy medications section.
Anyway, I found this post on www.hospitalsoup.com in the colonoscopy medications section.
jessica says:
I’m an internist and often request that patients undergo colonoscopy exams. I always thought that the sedation was to keep patients comfortable and that a qualified anesthesiologist would attend my patients. I’m shocked to find that many colonoscopy patients (most) undergo a brutal, painful and traumatizing exam without anesthesia, but inadequate “conscious sedation versed/fentanyl) administered not by an anesthesiologist. but by a nurse/crna who is not qualified to keep my patients comfortable. Colonoscopy patients often tell me that the nurse anesthetist doesn’t make the exam tolerable; they are thrashing about complaing of pain while a CRNA keeps telling then that “you are doing great”; administering an amnesia drug (Versed) in the hope that the unfortunate patient will forget how badly they were treated during the colonoscopy……. nurses (CRNA) are not qualified to administer any form of anesthesia..I will NOT recommend colonoscopy of any procedure requiring sedation unless an anesthesiologist (MD/DO) actually does the anesthesia 100% him/herself. I have too many patients who have had such a bad, dangerous experience with CRNA that they will NOT consider future lifesaving procedures,,,,
I promise the above is not me. However, it exactly parallels my thinking, so all you crna's who have called me various names, insulted my intelligence etc. can see that a doctor holds you in the same regard as I. That is; lower than dirt. I will never consider ANY procedure which involves sedation or an anesthesia nurse. I will make sure that the 'doctor' who wants to do my anesthesia is actually an MD doctor before proceeding. (As opposed to a nurse who has earned a doctorate in something other than medicine, like nursing or basket weaving, [HUMOR] you have to watch out for that one!) I may even have them sign a consent for ONLY an MD doctor's care prior to the procedure. I also want to avoid an assistant or other unskilled person performing my procedure. I'll put that right there with the "no sedation or Versed in any amount for any reason, before, during or after my procedure." Sorry to increase your workload MDAs but an anesthesia nurse is unacceptable to me for any part of my future procedures. Just like the internist above says.
My wonderful stepfather is also an internist, and he refuses Versed as well. He has noticed what a nurse friend of mine says, that is "every time one of my patients gets Versed, a little bit less of them comes back." Versed is tantamount to legalized torture, with the added fillip that we have to pay enormous amounts of money for this dubious "sedation" from an overpaid anesthesia nurse. Thanks Jessica for this post. We are RIGHT about this "medication" and crna's. (At least MOST anesthesia nurses. The good ones are the exception to the rule.)
Tuesday, March 19, 2013
Obamacare = $10,000 Per Illegal Alien
Not only do we have an out of control health care system, aided and abetted by Obama's "[un]Affordable Care Act" (actually a medical bailout) now we get to pay $10,000 per year for each illegal alien's health care. Did you know that? Our congressman told us all about it at his townhall meeting a couple of months ago.
Nobody has said or done anything about "bending the cost curve down" as promised. No, oh HELL no, we are just going to shift the burden of health care onto taxpayers, via exhorbitant new taxes, whether we can afford it or not! So now, when we working class stiffs are up at night worrying about the $20,000 dollars per year that the IRS says we should pay for health care, we get to fume over the fact that ILLEGAL ALIENS who are breaking the law by invading our country, tax evasion, identity theft,etc. all felonies by the way, we get to offer them 'free' health care which only costs US $10,000 EACH per year! Do the math. The government says that there are 12 MILLION illegal aliens here, probably more like 50 million if you factor in the way our government computes things! I think there are 12 million in Los Angeles county alone... What's not to like?
These aliens come in with all kinds of diseases, like the drug resistant tuberculosis, chagas disease, AIDS, typhoid, and on and on it goes. They spread it to us as well, so now everybody gets to have an expensive contagious illness. Only problem is that only illegal aliens can afford to have these diseases thanks to our elected officials deciding that we get to pay for THEM to have healthcare that WE can't afford for ourselves.
THIRD WORLD DISEASES MAKING A COMEBACK IN THE USA VIA ILLEGAL IMMIGRANTS
There has been zero legislation so far to rein in the excesses of our current health care delivery system. Not one single jot or tittle. Nothing about this absurd 'sedation for all' mentality, nothing about any QUALITY ASSURANCE to make sure that we aren't being killed, maimed or harmed by medical care. There is nothing about any 'mediation' processes whereby we patients can have some recourse when medical care harms us. Oh they want tort reform to leave us all helpless, but nothing to actually HELP with this crisis. There is nothing about the 'chargemaster' rip off scheme being dismantled. Nothing in there to cut back on the number of highly paid [so-called] professionals that are involved in patient care needlessly. The FDA is still fully funded by a corrupt big pharma industry.
The "Affordable Care Act" is one gigantic devastating boondoggle which will PREVENT anybody who actually works for a living from having health care. If you are middle class you are screwed. Poor people and illegal aliens will be leeching off of you, they get 'free' health care from YOU! The rich people have no problem paying for health care insurance of $20,000 a year like the IRS says. Just wait for the next wave of insurance premium hikes. Can't afford $20,000 now? You are going to have sticker shock when they start implementing this legislation. That is unless you are an illegal alien or one of the 'poor' folks.
If you have a job, get ready for it to be part time. Employers are eager to double their employee roster by dividing one full time job into two part time jobs. That way they can avoid the Affordable Care Act mandates. Kills two birds with one stone doesn't it? The unemployment rate will go down and the employer gets to stash whatever money they would have spent taking care of their full time employees. Don't ever believe that the Democrats aren't in the pockets of big business.
Why we couldn't have legislation that actually looked at why our health care is so expensive and instituted common sense reforms is beyond me. I guess they must be smarter than I am. Instead they bailed out the medical field and big business. Instead they encouraged more illegal immigration by offering free health care along with the rest of the basket of goodies, paid for by the working class of this country. More job security for the medical field by allowing illegal aliens in without health checks. More expense thrown up on the load that we are already carrying.
$10,000 DOLLARS PER YEAR, EACH, FOR ILLEGAL ALIENS TO COME HERE AND SPREAD THEIR DISEASE. THAT'S THE START, IT WILL GO UP FROM THERE. YOU AND I WILL PAY FOR THIS, FOR PEOPLE WHO SHOULDN'T BE HERE IN THE FIRST PLACE. Where are the news reports on this? We have Pravda US as a news system in this country. My own congressman says that if this $10,000 per year, each, illegal alien benefit were reported the people would be up in arms. And that, boys and girls, is why this is a secret from us.
Sunday, March 17, 2013
Another Blog About Medical [non] Care
I got an e-mail from a friend of mine who blogs here;Hysterectomy Information - Home
Included in the e-mail were links to yet another medical care sufferer. Losing My Leg To A Medical Error. - Medical Office Group.: Ashworth College Community His story scares me on a personal level because my crna Aaron saw no problem with cranking down a pressure cuff on my upper arm to the point that for weeks/months afterward I experienced excruciating pain from it. The pressure cuff caused more pain than the botched surgery and was right up there with the pain I experienced from the kidney infection I got from the hospital. The pain was worse than the nerve pain from my ulna where my esteemed surgeon (or another) had left a LOCKING screw head loose and interfering with my ulnar nerve. (I emphasize LOCKING screw because I fail to understand how a LOCKING screw could rotate out of the bone and into my ulnar nerve. That really can't happen; I work with locking screws all the time and have NEVER had one back out, regardless of a vibration level far in excess of anything that happens inside the human body. My surgeon (or the janitor) HAD to have installed it that way.)
According to this doctor, I may eventually need to have my arm amputated. I have moderate numbness in my hand, that I assumed was from the doctor (or janitor) "tugging on the nerves" as my surgeon put it, during my ORIF distal radius surgery. Now I find out that the pressure cuff could actually have caused more damage than I ever imagined.
Aaron the crna, had use of a pressure cuff that could be inflated and deflated by a dual mechanism. I didn't know this until my second surgery to correct the major defects in the first. Apparently the pressure cuff contains two pressuring devices side by side. That way the cuff can be inflated in an adjacent area and deflated in the other in order to provide relief from a single pressure point. My second crna did this for me. When the pain became too great, he simply moved the pressure point. (In this second surgery I was NOT knocked out, nor sedated as per my instructions. Amazing that one crna understood me and Aaron couldn't!)
Aaron obviously didn't care to do this for me. After all, he had sedated me and knocked me out without permission and against my will, so OBVIOUSLY he didn't give a damn about what was "best" for me to start with. I'm sure he kept up his insulting chit-chat about me, while ignoring the potential for harm from him clamping down on my arm so severely and leaving it in that one spot for the duration of the surgery.
BTW the excuse I got for the trauma to my upper arm was that my blood pressure shot up (after Versed) and that the cuff had to be extra tight in order to combat that. My muscles actually drooped from the crushing of the pressure cuff. It was startling to me and even to my surgeon when I lifted my arm and displayed the droop.
The moral of this story is, don't ever trust medical people. Stay awake, without amnesia (that's for medical people who redefine the English language) if at all possible. That way if something hurts they will rectify it instead of leaving you suffering and causing yet more problems for you. After all, as this doctor says, the amputation cost $150,000 and the artificial limb cost another $50,000. We truck drivers have a saying for this kind of misbehavior and it's called, "job security." Don't allow them to use YOU AND YOUR BODY for their "job security"!
Ever Heard About The "Chargemaster"?
I had never heard about a "chargemaster"! The "chargemaster" is the internal billing scheme used by hospitals and medical treatment facilities to fleece the public out of billions of dollars. You really need to watch the video contained in this piece! The article in it's entirety is worth reading, the contents will shock you... No wonder 60% of all bankruptcies are from medical care. And it's all UNNECESSARY! Hospitals are raking it in, making massive profits at our expense. It surely isn't because of the stellar care that we are [not] receiving. Iatrogenic medical deaths are the number 1 leading cause of death in this country regardless of the outrageous and unsustainable costs associated with medical care.
The Absurd Costs of American Health Care
Also worth watching is this video, linked obscurely on the site:Suzanne Somers Throws Knockout for Cancer - YouTube#at=520#!
Of particular note for me was Suzanne's take on mammograms which follows exactly what I have been saying on this blog. She also takes on the ubiquitous and misnamed "Standard of Care" which many places point to as their wonderful blueprint of patient care, which is actually a bogus claim. The only "standard of care" that I see is the standard of caring for medical workers and medical centers, the patients be damned.
Subscribe to:
Posts (Atom)